
MIPS Reporting That Clears 75 — and Keeps the −9% Off Your Remittance
The threshold is 75 points, locked through at least 2028. The penalty is up to −9% on every Medicare Part B payment, two years after the mistake. RevGen runs the whole performance year for you — eligibility, measure selection, attestation, submission, and score defense — so the number is never a surprise.
- The score math run all year, not discovered at submission: 6 quality measures incl. 1 outcome measure, 75% data completeness, benchmark-checked before it counts
- 2026 deadlines enforced for you: Improvement Activities underway by Oct 3, 2026 · MVP registration by Nov 30, 2026 · submission closed by Mar 31, 2027
- The MVP decision made deliberately: 27 MVPs for 2026 (6 new) vs. traditional MIPS — with CMS signaling traditional-MIPS sunset, we run the comparison both ways before you commit
- All four categories handled: Quality, Cost strategy, PI attestation (2025 SAFER Guides, tightened Security Risk Analysis, optional TEFCA bonus measure), Improvement Activities
- Correct mechanisms only: registry, QCDR, eCQM, or claims — the retired CMS Web Interface stays off your plan
- Free MIPS audit first — eligibility, current scoring position, and the exact work required, before you spend anything
What MIPS Is — The Four Categories, the 2026 Weights, the Real Minimums
MIPS (the Merit-based Incentive Payment System) is CMS’s quality-reporting program under the Quality Payment Program: your performance across four categories produces a composite score from 0–100, compared against a threshold, that adjusts every Medicare Part B payment two years later. Here’s the 2026 structure with the minimums most pages leave out.
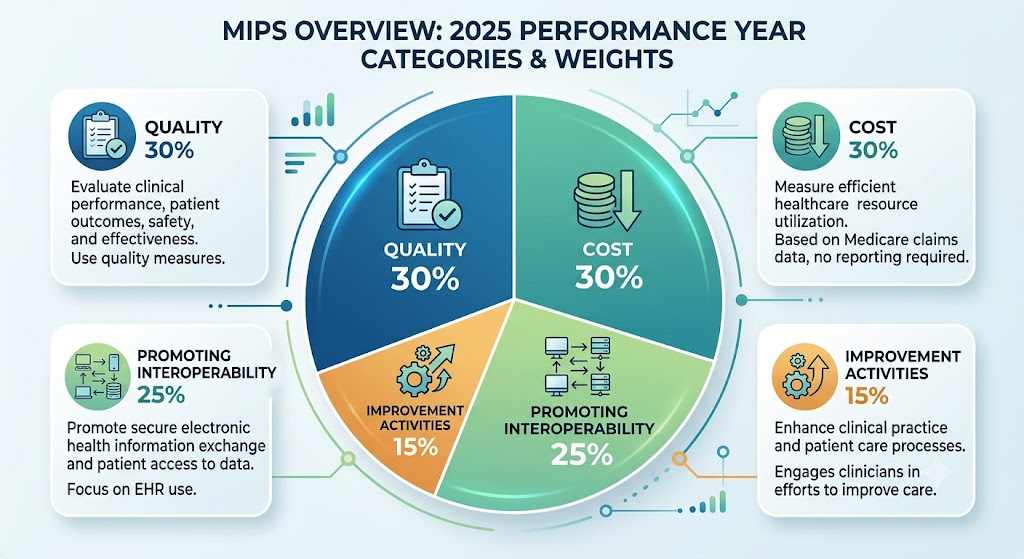
| Category | 2026 weight | What it measures | Minimum performance period | How it’s reported |
|---|---|---|---|---|
| Quality | 30% | Clinical performance on 6 selected measures, incl. ≥1 outcome or high-priority measure; 75% data completeness and 20+ cases per benchmarked measure | Full calendar year | Claims, registry, QCDR, or eCQM |
| Cost | 30% | Spending vs. peers across 35 measures — total per-capita cost (updated attribution) and episode-based measures | Full calendar year | Nothing — CMS calculates from claims |
| Promoting Interoperability | 25% | Certified EHR use: e-prescribing, health information exchange, provider-to-patient exchange, public health reporting — plus the 2026 additions below | Any 180 continuous days | Attestation via CEHRT |
| Improvement Activities | 15% | Care coordination, safety, equity, patient engagement — ~100 activities (2 required; 1 for small practices) | Any 90 continuous days | Attestation |
Scoring boosts most practices don’t claim
Small practices (≤15 clinicians) earn +6 bonus points automatically. The complex-patient bonus adds points for treating high-risk Medicare populations. And the improvement score compares you to your own prior performance — not just national benchmarks. All three are calculated by CMS after submission, but only if the underlying data supports them. We build all three into measure strategy from January, not March of the submission year.
The 2026 Scoreboard — What Held, What Moved
CMS deliberately kept the 2026 framework stable — which makes the changes that did land easy to miss. Here’s the full delta.
UnchangedThe stable core
✦ Performance threshold: 75 points — CMS committed through at least the 2028 performance year
✦ Category weights: Quality 30% · Cost 30% · PI 25% · IA 15%
✦ Low-volume threshold: $90K allowed charges · 200+ patients · 200+ covered services
✦ Adjustment range: ±9% — penalties linear to the full −9% at a score of 18.75 or below
New for 2026What actually changed
✦ Quality measure set: 187 measures (5 new, 10 removed, 30 updated)
✦ PI: Security Risk Analysis now requires a risk-management attestation; 2025 SAFER Guides required; new optional TEFCA bonus measure
✦ IA: inventory refreshed (~100 activities; “Achieving Health Equity” subcategory → “Advancing Health and Wellness”)
✦ Cost: 35 measures, updated TPCC attribution, 2-year informational period for future measures
✦ MVPs: 27 available (6 new, 21 modified)
Stability is not the same as safety
A frozen threshold with tightening benchmarks and refreshed measure sets means the margin for error moved even though the number didn’t. Measures removed from the 2026 set can’t be reported; updated specifications change what counts as a performance denominator; and PI’s new attestation requirements trip practices that recycled 2025 worksheets. Stable program, moving goalposts — the score is decided by data discipline, and that’s exactly what a reporting partner is for.
Live Calendar — as of late September 2026
The 2026 Deadlines That Decide Your 2028 Payments
MIPS consequences arrive two years late — which is why practices discover a −9% adjustment on a remittance instead of a deadline calendar. Here is the one that matters now, in order:
already passed
Latest compliant PI start. Promoting Interoperability requires 180 continuous days — the final possible window opened July 5. If your PI attestation isn’t already running, the 2026 PI category needs a documented reweighting or hardship pathway, not hope.
days away
Improvement Activities start deadline. 90 continuous days must fit before December 31 — activities not underway by October 3 cannot complete. Two activities (one for small practices), chosen and documented now.
MVP registration deadline. Reporting a MIPS Value Pathway for 2026 requires CMS registration — the window opened April 1 and closes November 30. After that, it’s traditional MIPS for 2026.
Performance year closes. Quality data must cover the full calendar year at 75%+ completeness — there is no partial-year Quality rescue.
Submission window. Data goes to CMS via registry, QCDR, eCQM, or claims. Errors caught during the window can be corrected; after March 31, 2027, nothing changes.
Payment adjustment lands. Your 2026 composite score becomes a payment adjustment on every Medicare Part B claim — positive, neutral, or up to −9% — for the full year.
Reading this after October 3?
Half a performance year is still more than zero: Quality measure selection, data completeness, Cost-influencing coding discipline, and every remaining attestation window are all still in play — and 2027 planning starts now. A late audit beats a March 2027 surprise every time.
Who Has to Play — The Three-Prong Test Most Pages Get Two-Thirds Right
Participation is mandatory only if a clinician exceeds all three low-volume prongs. Exceed just one or two, and you may opt in. Fall below any one, and you’re excluded — an exclusion that should be confirmed and documented, not assumed.
| Prong (both determination periods) | Threshold |
|---|---|
| Medicare Part B allowed charges | > $90,000 |
| Medicare Part B patients | > 200 |
| Covered professional services the prong everyone forgets | > 200 |
Eligibility is measured across two 12-month determination periods (Oct 1, 2024–Sep 30, 2025 and Oct 1, 2025–Sep 30, 2026 for the 2026 performance year) — you must exceed the thresholds in both to be automatically included. Clinicians in their first year of Medicare Part B participation are exempt.
Who’s in the pool now
Physicians, PAs, NPs, clinical nurse specialists, CRNAs, physical and occupational therapists, speech-language pathologists, audiologists, psychologists, clinical social workers, registered dietitians/nutrition professionals — and, added in recent years, marriage and family therapists and mental health counselors. Most practices missed at least one of these additions.
The APM angle
Clinicians in qualifying Advanced APMs report through the APM Performance Pathway, not traditional MIPS — and qualifying APM participants are exempt from MIPS adjustments entirely. Confirming which side of that line you’re on is step zero; misclassifying it is the most expensive eligibility error there is.
The MVP Decision — Optional in 2026, the Default Once Traditional MIPS Sunsets
MIPS Value Pathways replace the pick-any-6-measures buffet with a specialty-aligned bundle: fewer quality measures that fit how you actually practice, plus a population-health measure, the Cost category, and a curated set of improvement activities and PI requirements.
| Option | Best for | 2026 fine print |
|---|---|---|
| Traditional MIPS | Maximum measure choice; multi-specialty flexibility; first-time reporters | Still fully available — but CMS has signaled its intent to sunset traditional MIPS, proposed to begin with the 2029 performance year |
| MIPS Value Pathway | Specialty-aligned reporting with fewer, coherent measures | 27 MVPs for 2026 — six new: Diagnostic Radiology, Interventional Radiology, Neuropsychology, Pathology, Podiatry, Vascular Surgery · registration by Nov 30, 2026 · multispecialty groups (non-small) must report as subgroups or individuals |
| APM Performance Pathway | Clinicians in qualifying APMs (e.g., MSSP ACOs) | 3 required quality measures instead of 6; the mandatory route for MSSP ACOs since the CMS Web Interface retired |
Our position on MVPs
The right MVP simplifies reporting and aligns your score with your real practice. The wrong one just constrains measure selection without improving it. Because MVP selection locks at registration, we model both paths — traditional and MVP — against your actual patient data before you commit, and we start clients on MVP mechanics now while the choice is still voluntary. When traditional MIPS sunsets, our clients will already be fluent.
Submission Mechanisms — Four Current Options and One Retired Ghost
How your data reaches CMS changes what’s possible: measure choice, scoring headroom, and who can report. This is also where stale advice is easiest to spot.
Claims
Quality-only via Medicare Part B claims; individual clinicians only. Simple, but the ceiling on scoring makes it a last resort for anyone with real Medicare volume.
Qualified registry
The workhorse: full quality-measure coverage, benchmark feedback, and validation before submission. Right for most groups.
QCDR
Everything a registry offers plus custom non-MIPS measures — often the strongest option for specialties with thin standard measure sets.
Direct EHR / eCQM
Electronic clinical quality measures straight from your certified EHR — powerful when data mapping is done right, garbage when it isn’t.
⚠️ The retired mechanism still being recommended
The CMS Web Interface — the old groups-of-25+ reporting route — retired from traditional MIPS after the 2023 performance year and from ACO reporting after 2024 (ACOs moved to the APP). If a consultant or billing company still lists it as your submission path, they’re working from guidance that is two-to-three years out of date. Large groups now report through registries, QCDRs, or eCQMs like everyone else. Stale mechanism advice is the clearest possible signal to get a second opinion.
How RevGen Runs Your MIPS Year — Seven Steps, Zero Surprises
Not submission-only. We own the performance year itself, because that’s where the score is actually made.

Eligibility & pathway confirmation. Every clinician checked against all three low-volume prongs across both determination periods — MIPS-eligible, excluded (documented), opt-in candidate, or APM/APP side of the line. Misclassification is the most expensive error in the program; we clear it first.
Measure selection with benchmark data. Six quality measures chosen for your specialty and your actual patient population — each checked against its benchmark, decile ceiling, and data-completeness feasibility before it makes the list. MVP vs. traditional modeled both ways.
Data collection inside your EHR. Workflows and capture rules configured in your system (any of 40+ platforms) so completeness runs at 75%+ from January — not reconciled in a panic in March.
PI attestation managed. CEHRT capability review, the four objectives, the tightened Security Risk Analysis with risk-management attestation, 2025 SAFER Guides — plus the optional TEFCA bonus measure where your exchange setup supports it. 180-day window planned, not improvised.
Improvement Activities documentation. Activities you already genuinely perform, identified and evidenced — started by the October 3 deadline, sized for small-practice rules where they apply.
Submission via the right mechanism. Registry, QCDR, eCQM, or claims — chosen for your measure set and group structure, submitted well before the March 31, 2027 close, with errors corrected inside the window.
Score monitoring and defense. Preliminary scores tracked through the submission window; target reviews and resubmissions where the rules allow; then next-year strategy built from what the data actually showed.
What the free MIPS audit covers
Eligibility status for every clinician · your current scoring position against the 75-point threshold · category-by-category gap analysis (including whether your PI window is already in trouble) · MVP vs. traditional recommendation · and a fixed quote for the work. No obligation, no migration, no speeches.
Already Penalized? Here’s the Honest Recovery Path
The pattern is remarkably consistent: a practice notices Medicare payments landing below contracted rates, pulls the remittance, and finds a payment-adjustment factor applied to every Part B line — traced to a reporting year two prior. By then the window to contest is closed.
What can’t be fixed
A finalized adjustment stands. There is no retroactive appeal that reopens a closed performance year — anyone selling one is selling hope.
What can be checked
Whether the penalty was correctly applied. Misapplied adjustments and misclassified eligibility are real, documented occurrences — the first thing we verify.
What can be fixed
The cause. We diagnose what produced the score — measure selection, data completeness, missed attestation, eligibility error — and run the current year so 2028-and-beyond adjustments return to neutral or positive.
Where MIPS Fits in Your Revenue Operation
MIPS is one leg of the Medicare stool — quality reporting on top of the billing that earns it, in the EHR that runs it. The rest of the system:
Frequently Asked Questions
The questions practices actually ask about MIPS — with the numbers, dates, and mechanisms named. (This FAQ also ships with structured schema markup for search visibility.)
What is the MIPS performance threshold for 2026?
What are the four MIPS categories and their 2026 weights?
Who is required to participate in MIPS?
What are the key MIPS deadlines for the 2026 performance year?
What is an MVP, and should we report one instead of traditional MIPS?
Does my EHR automatically handle MIPS reporting?
How is the Cost category scored if we don’t submit anything?
What are the reporting mechanisms for MIPS quality data?
What happens if we don’t report MIPS?
Can we still fix our 2026 MIPS score if we’re starting late?
Can RevGen fix a MIPS penalty from a prior year?
How much do MIPS reporting services cost?
Where Does Your MIPS Score Stand Right Now?
Free audit: eligibility for every clinician, your position against the 75-point threshold, the PI-window check, and the MVP-vs-traditional recommendation — before the October 3 Improvement Activities deadline passes.
Request Your Free MIPS Audit →October 3 and November 30, 2026 deadlines are closer than they look. March 31, 2027 is final.