
Revenue Cycle Management Services That Actually Move the Needle
The Whole Revenue Cycle, Run as One System — With Numbers You Can Verify
RCM breaks down in most practices for one reason: fragmentation — different hands at every stage, nobody owning the handoffs. RevGen runs all eight stages as one workflow inside your EHR, measured against KPIs with published formulas, and kept current with every 2026–2027 Medicare change that touches the cycle.
- All 8 stages owned: patient access, prior authorization, charge capture, submission, denial management, payment posting, patient billing, reporting — no orphaned handoffs
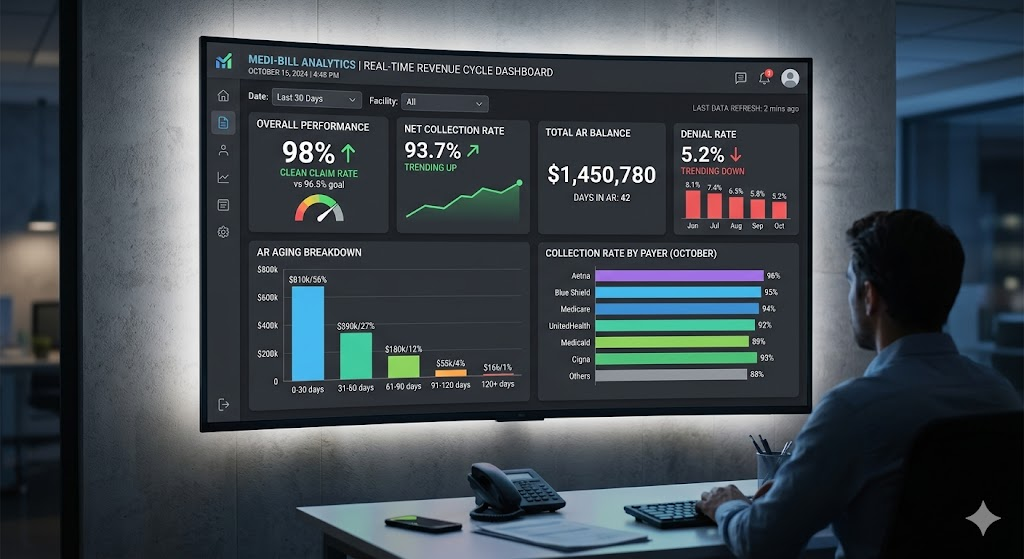
- KPIs with formulas: first-pass clean claim rate ≥95%, net collection rate ≥96% of contracted, days in A/R <35 — defined on the page, verifiable in your system
- 2026 handled: G2211 capture, the fee-schedule conversion-factor cut, CMS-0057-F prior-auth clocks (72 hours / 7 days), telehealth billing through 2027
- January 1, 2027 readiness: charge-master currency checks against CPT 2027 and the maternity global deletion — before January turns stale codes into denials
- Your EHR stays: the full cycle runs inside any of 40+ platforms — no migration, no lock-in, your data in your system
- Free audit first: baseline numbers, leak map, and the KPI gap — in writing, yours to keep
What Revenue Cycle Management Is — And Why It Breaks Down
The cycle starts before the patient walks through the door and ends when every dollar from the encounter is either collected or written off with a documented reason. Everything in between is a handoff — and handoffs are where practices bleed.
The reason it breaks down in most practices isn't complexity — it's fragmentation. Different staff handle different stages with no unified workflow or accountability. A registration error creates a coding conflict, which generates a denial nobody works, because the A/R follow-up process doesn't exist in any systematic way. Full-service RCM eliminates the handoff failures: every stage owned by a specialist, monitored against defined metrics, reported back to you in real time.
The 8-Stage Cycle — Each Stage, Its Failure Point
Six stages are the classic cycle. We run eight — because prior authorization and reporting each deserve to be run as first-class stages, not afterthoughts.
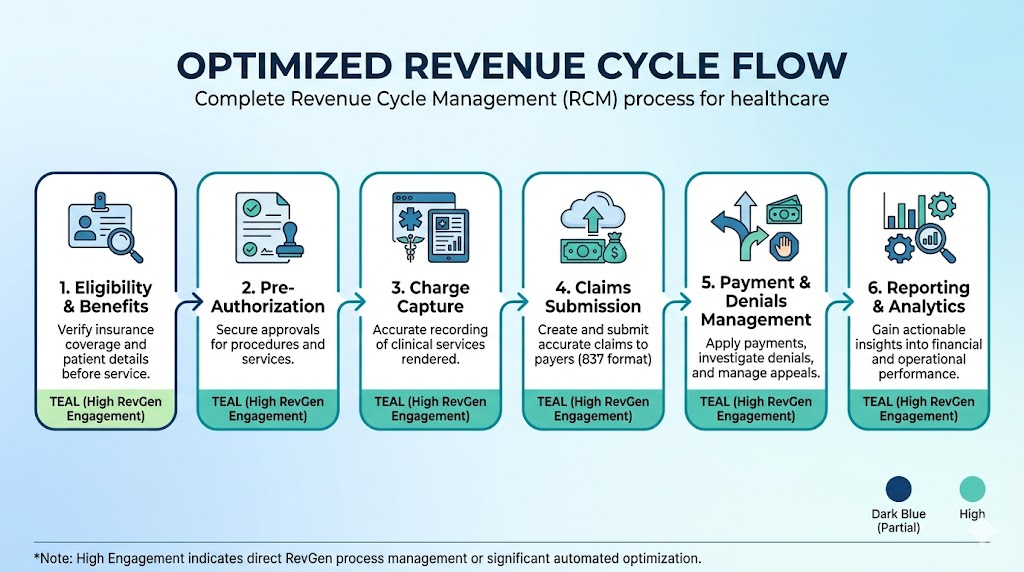
| Stage | What we do | The failure point it prevents |
|---|---|---|
| 1. Patient access & eligibility | Real-time coverage, benefits, copay and deductible checks before every visit | Coverage lapse caught at the front desk instead of as a CO-27 denial |
| 2. Prior authorization stage, not afterthought | Requirements tracked by payer and CPT code; packets built before treatment; turnaround monitored against the 2026 legal clocks (72 hrs expedited / 7 days standard) | CO-197 auth denials — and "still pending" excuses that no longer fly |
| 3. Charge capture & coding | Certified coders review documentation against current CPT/ICD-10/HCPCS; undercoded and overcoded encounters flagged pre-submission; G2211 appended where the longitudinal relationship supports it | Silent underbilling — the claim that pays, at the wrong amount |
| 4. Claim submission | Automated pre-submission edits (NPI, taxonomy, modifier compatibility, payer formatting) with human review where judgment matters | Rejections for missing fields and wrong formats |
| 5. Denial management | Every denial categorized by CARC family and root cause; appeals filed within level deadlines; patterns fed back upstream | Denials aging past timely filing into write-offs |
| 6. Payment posting | Daily ERA posting, line-level reconciliation against contracted rates, underpayments flagged | "Phantom open claims" and an A/R report you can't trust |
| 7. Patient billing | Clear statements timed to secondary completion; payment plans and portal payments | Confusing bills that go unpaid and damage the relationship |
| 8. Reporting & KPIs | Live dashboards plus the four formula-defined KPIs below, monthly root-cause reviews | Flying blind — no baseline, no trend, no accountability |
The classic example of stage-3 leakage
A physician documents a 45-minute visit addressing two separate problems. The claim goes out as a 99213. The documentation supported a 99214 — and with modifier -25, a separately billable procedure. That gap, multiplied across hundreds of visits a month, is real revenue that never appears on any denial report, because the claim paid — just at the wrong amount. Undercoding is invisible to denial metrics and only shows up in a coding-pattern review. Ours runs continuously.
The KPI Dashboard — Four Numbers, Four Formulas
RCM without defined metrics is billing with extra steps. These are the four numbers we report, how they're calculated, and what "good" looks like — the same definitions used across our audit, denial, and specialty pages.
| Metric | Formula | Target |
|---|---|---|
| First-pass clean claim rate | Claims accepted on first submission ÷ total claims submitted — measured before rework | ≥ 95% |
| Net collection rate | Payments ÷ (charges − contractual adjustments) | ≥ 96% of contracted rates |
| Days in A/R | Total A/R ÷ average daily charges | < 35 days |
| Denial rate | Claims denied ÷ claims submitted, root-caused monthly by payer and CARC family | < 5% |
Why the formulas are published
Published industry averages for clean claim rates vary by specialty and measurement method — and a rate measured after rework is not a first-pass rate. Any billing company can quote a impressive-sounding percentage; the test is whether they'll define it and let you reproduce it in your own system. Every number in our dashboards passes that test — that's what "managed revenue cycle" means as opposed to "we send your claims."
Why 2026 Made the Cycle Harder to Run In-House
Five changes landed on the revenue cycle in 2026–2027 — each one hits a different stage, and together they've raised the bar for what "managing the cycle" actually requires.
📉 Fee-schedule pressure (all stages)
Medicare's 2026 Physician Fee Schedule conversion factor came in lower (roughly $33.40) with a phased efficiency adjustment continuing — same work, tighter margin. Undercoding, missed add-ons, and unworked denials are now proportionally more expensive than ever.
➕ G2211 capture (stage 3)
The refined visit-continuity add-on pays for exactly what longitudinal practices sell — but only when charge capture appends it correctly. Most in-house workflows miss it entirely; it's become one of the largest silent underbilling gaps.
⚡ Prior-auth clocks (stage 2)
Under CMS-0057-F, since January 1, 2026 MA/Medicaid/CHIP payers must decide expedited auths in 72 hours and standard in 7 days, with specific reasons for every denial — and electronic prior-auth APIs go live January 1, 2027. Auth tracking is now deadline-enforcement work.
🔌 The interoperability data layer (stages 2–4)
USCDI v3 became the certified-EHR baseline January 1, 2026, and FHIR-based exchange is now an enforceable right under information-blocking rules. A modern RCM operation reads the same data rails your EHR does.
🗓️ January 1, 2027: the code wave (stage 3)
CPT 2027 lands and the maternity global-period codes are deleted, restructuring pregnancy billing. Charge masters that aren't checked in December produce automatic denials in January. Our charge-master currency check runs against the full 2026→2027 delta — it's part of the free audit, not an upsell.
Three Ways to Run the Cycle — The Honest Comparison
| Model | What it covers | 2026 economics | What breaks |
|---|---|---|---|
| In-house billing | Whatever one overloaded staffer can reach — usually submission and posting, rarely root-cause denial work or KPI reporting | A billing-capable hire runs $45K–$60K+ salary (2026 market) plus 25–30% overhead load, before software and training | The single point of failure: one vacation, resignation, or busy season stalls the whole cycle — and the knowledge leaves |
| Billing-only service | Claims out and payments posted — the middle of the cycle | Lower percentage, but eligibility, auths, denials-depth, and reporting are typically "not our job" | The two ends of the cycle: front-end denials nobody prevents, back-end A/R nobody works |
| Full-cycle RCM RevGen | All 8 stages, in your EHR, with KPI reporting and 2026–2027 currency built in | Typically 4–9% of net collections (per-claim/hybrid available); no setup fees, no contracts | Nothing structurally — and you can verify every number in your own system |
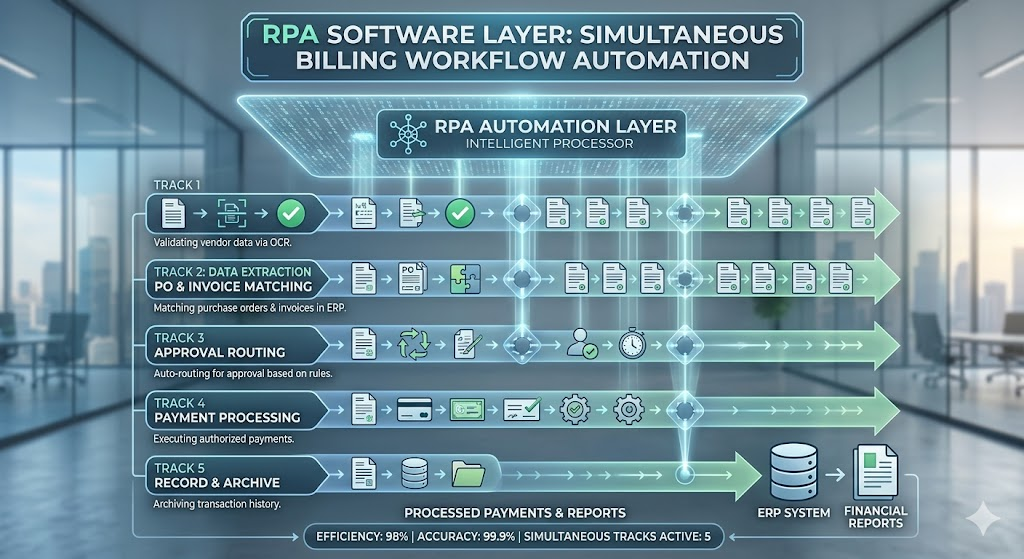
Why "claims go out clean" isn't enough
The most common question in physician billing forums: "Why is my A/R aging getting worse even though my claims go out clean?" The answer is almost always downstream — payment posting errors creating phantom "open" claims, and no systematic follow-up on the claims that did go out wrong. Clean submission is necessary but not sufficient. The back end of the cycle matters just as much as the front, which is why "billing" keeps your A/R a mystery and "RCM" keeps it worked.
Onboarding — Two to Three Weeks, Real Dates
Free audit & baseline. KPIs measured with formulas, leak map by stage, legacy A/R sized — in writing.
Configuration. Account built around your specialty, payer mix, EHR, and provider roster; BAA executed; named-user access provisioned.
Credentialing review + workflow build. Enrollments verified, renewals flagged; stage workflows and scrubber rules mapped to your platform.
Go-live. First claims through dual QA; daily posting begins; dashboard access from day one. A real calendar date, sized to your payer count and A/R depth.
Pricing — Tied to Collections, Not Claims
% of net collections
Typically 4–9% of what's actually collected — incentives aligned: we earn when you collect. Scope, specialty mix, and volume set the exact rate, quoted after the audit.
Per-claim & hybrid
Flat per-claim for uniform small practices; hybrid base + reduced percentage when you keep front-end in-house. We show the math both ways — including the minimum-fee trap percentage agreements can hide.
Always included
No setup fees · no long-term contracts · denial rework included · credentialing included · legacy A/R worked · weekly KPI reporting.
The Rest of the System
The revenue cycle is the spine; these pages are the organs — each one goes deeper where this page stays broad:
Frequently Asked Questions
What is revenue cycle management?
How is RCM different from just billing?
What is a good clean claim rate?
What KPIs should RCM reporting show?
Can we keep our existing EHR?
How does RCM handle prior authorization in 2026?
What changed in Medicare's 2026 fee schedule that affects the revenue cycle?
How much does revenue cycle management cost?
How long does RCM onboarding take?
Can RevGen handle credentialing for new providers?
Does RevGen offer MIPS reporting?
What should practices check before January 1, 2027?
See Your Cycle, Stage by Stage — Free
The free RCM audit baselines all four KPIs, maps your leaks by stage, sizes the recoverable dollars in aged A/R, and checks your charge master against the January 2027 changes. In writing, yours to keep.
Request Your Free RCM Audit →✔ 24–48 hour findings · ✔ No obligation · ✔ Your current biller is never contacted