
Why Claim Denials Are Costing You More Than You Think
Every Denial Categorized, Worked, Appealed — Before the Clock Runs Out
A denial is a decision, not a verdict — most are reversible inside windows that quietly expire. RevGen runs denial management as a system: CARC-coded root-cause analysis, deadline tracking per payer, appeals through every level, and the upstream fixes that stop the same denial from returning next month.
- Root-cause, not resubmission: every denial categorized by CARC family, payer, code, and provider — the pattern gets fixed upstream, not re-worked forever
- 2026 rules used for you: since Jan 1, 2026, MA/Medicaid payers must decide prior auths in 72 hours (expedited) / 7 days (standard) and give a specific reason for every denial — specific reasons build stronger appeals
- The full appeals ladder worked for you: redetermination → QIC → ALJ → Appeals Council, with every level’s filing deadline tracked
- Both clocks tracked: timely filing windows and appeal deadlines are separate clocks per payer — conflating them is how recoverable money gets written off
- Denial KPIs with formulas: denial rate, overturn rate, and denial aging — defined, reported, verifiable in your system
- Free denial audit first — your biggest denial categories and the recoverable dollars in aged A/R, in writing
Why Denials Are Costing You More Than You Think
There’s a number most practice managers never calculate: the annual revenue written off not because claims couldn’t be paid, but because nobody followed up in time. In the practices we’ve audited, it’s rarely coding errors — it’s denials that aged past timely filing because a denial management workflow didn’t exist.
A denial is not a rejection. A rejection is bounced before adjudication — bad format, invalid member ID, missing field — fixable and resubmittable in days. A denial is an adjudicated decision by the payer not to pay, delivered with a CARC code and appeal rights. That decision is often reversible with the right documentation and the right appeal, filed inside the right window. The problem is that the window closes — and once it closes, the revenue is gone. Systematic denial management makes sure nothing ages past it: every denied claim reviewed, categorized, corrected, resubmitted or appealed before the clock runs out.
The distinction that gets practices paid
Managing rejections and denials as one undifferentiated pile is how deadlines get missed: rejections feel urgent (the claim “failed”) while denials feel final (the payer “decided”) — so rejections get fixed and denials get filed away. The truth is the reverse of the instinct: the rejection has no money attached yet, and the denial has money and a countdown attached.
The Eight Denial Categories — With the CARC Codes That Name Them
Denials come to you as CARC (Claim Adjustment Reason Code) families on the remittance. A billing partner should speak that language fluently — here are the eight categories that cover the overwhelming majority of denials, and the prevention for each.
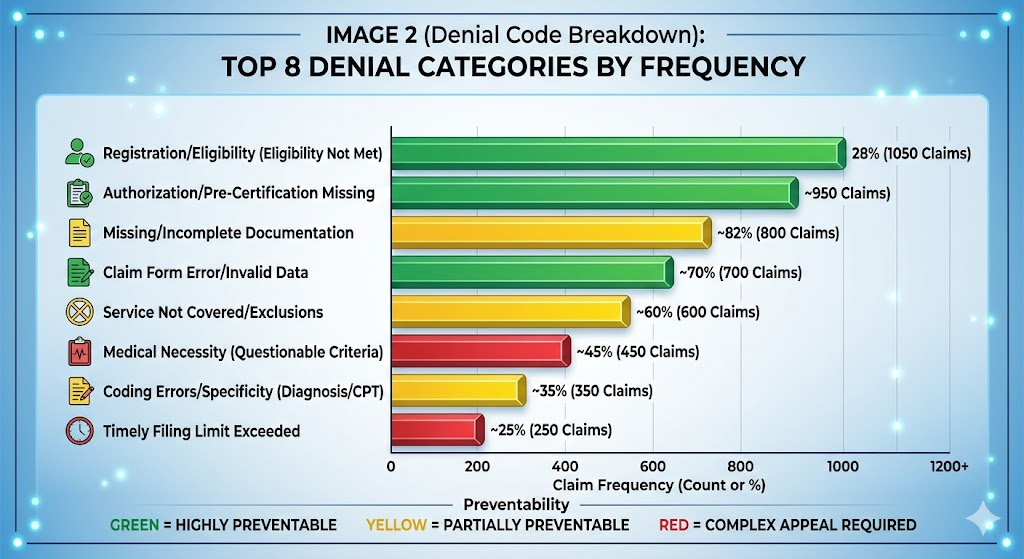
| Category | Typical CARC | What it means | Prevention |
|---|---|---|---|
| Eligibility / coverage | CO-27 | Coverage lapsed or the plan doesn’t cover the service | Real-time eligibility verification before the visit |
| Authorization missing | CO-197 | Prior auth not obtained or not on file for the DOS | Auth tracking tied to scheduling, with alerts |
| Coding / missing info | CO-16 | Claim lacks information or has a coding inconsistency | Certified coder review + scrubber rules before submission |
| Modifier inconsistent | CO-4 | Procedure code inconsistent with the modifier (-25/-59 misuse) | Documentation-first modifier review; recurring CO-4s = template problem |
| Timely filing | CO-29 | Submitted past the payer’s filing window — non-appealable | Claims out within 24–48 hours of service; denial clock tracking |
| Duplicate claim | CO-18 | Same service submitted twice | Duplicate detection before submission |
| Medical necessity | CO-50 | Documentation doesn’t support the diagnosis/service | Pre-submission clinical documentation review against LCD/NCD criteria |
| Bundling / NCCI | CO-97 | Service bundled into another paid service per NCCI edits | NCCI pair checks and modifier discipline at charge entry |
| COB / other payer | CO-22 · PR-22 | Another payer is primary; payer order incorrect | COB verification during eligibility, before the claim goes out |
| Credentialing gap | rejection: “provider not on file” | Rendering provider not enrolled with the payer | Enrollment verification + renewal tracking 90 days ahead |
Reactive vs. Proactive — Resubmission Is Not Denial Management
Most billing companies operate reactively: a claim denies, someone reads the code, corrects the obvious error, resubmits. That doesn’t reduce your denial rate — it processes the same denials month after month, indefinitely.
Proactive denial management tracks patterns across payers, procedures, and providers. If CO-4 denials cluster around one CPT code with one payer, that’s a systemic problem, not eighty separate one-offs. Fix the template, the training, or the scrubber rule and the denial stops recurring. Reactive management keeps you busy; proactive management reduces the workload — that’s the difference between treating symptoms and treating the disease.
The forum question that captures it
A recurring question in billing communities: “We’re resubmitting denied claims but our denial rate isn’t improving — what are we doing wrong?” The answer is always the same: resubmission is not denial management. Real denial management categorizes every denial by root cause, tracks frequency by payer and code, and feeds that analysis back into the submission workflow. Without the feedback loop, you resubmit the same denials forever.
Live now
The 2026 Rules That Changed Denial Management — And How We Use Them
The CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F) regulates payers — Medicare Advantage organizations, Medicaid and CHIP plans, and exchange Qualified Health Plans (traditional Medicare is not covered) — and its provisions phased in across 2026 and 2027 reshape what denial management can accomplish.
Since Jan 1, 2026
Covered payers must decide prior-authorization requests within 72 hours (expedited) or 7 calendar days (standard) — and every denial must state a specific, actionable reason, regardless of how the request was submitted. No more “not medically necessary” as the entire explanation.
By Mar 31, 2026
Payers posted their first public prior-auth metrics (covering 2025 data) — denial rates, timeliness, and appeal outcomes now sit on their websites. Public accountability is a negotiation lever most practices never pull.
Jan 1, 2027
Four FHIR-based APIs go live — including a standard electronic Prior Authorization API replacing fax-and-portal workflows — and MIPS-eligible clinicians begin electronic prior-authorization attestation (a new Improvement Activities avenue; see our MIPS page).
What this means for your denials
- Specific denial reasons are appeal ammunition. A denial that must state its exact reason hands you the exact counter-argument. We build appeals off the payer’s own stated criteria.
- 72-hour decisions kill the “still pending” excuse. Auth status is now a trackable SLA — when a payer blows it, that’s leverage on the appeal and a documented pattern.
- Public metrics create accountability. Payers are now publicly measured on prior-auth denials and appeal overturns. Practices that cite a payer’s own published metrics in escalations get different outcomes than practices that ask nicely.
- 2027 makes electronic prior auth the default path — EHR-integrated submission and response tracking instead of fax archaeology. Your billing partner should be FHIR-fluent before then, not after.
The Appeals Ladder — Five Levels, Real Deadlines, Tracked Per Claim
You can’t appeal what you don’t track, and you can’t track deadlines you don’t know. The original Medicare ladder, with the clocks that matter:
| Level | Who decides | File within | Decision within |
|---|---|---|---|
| 1 | Redetermination — fresh review by the Medicare Administrative Contractor (MAC) that processed the claim | 120 days of the initial determination | 60 days |
| 2 | Reconsideration — Qualified Independent Contractor (QIC); independent clinical review — the stage where the complete record belongs | 180 days of the redetermination | 60 days |
| 3 | ALJ hearing — Administrative Law Judge, Office of Medicare Hearings and Appeals; evidence and testimony | 60 days · 2026 amount-in-controversy threshold: $200 | 90 days (statutory target) |
| 4 | Medicare Appeals Council review | 60 days | varies |
| 5 | Federal district court | 60 days · higher amount-in-controversy threshold | — |
Medicare Advantage runs its own track: generally 60 days from the plan’s denial to request a Level 1 reconsideration by the plan itself, then escalation to an independent review entity — and MA appeal outcomes are exactly where the OIG data below comes from.
The OIG findings every practice should know
HHS Office of Inspector General, on Medicare Advantage denials:
- When beneficiaries and providers appealed, MA plans overturned 75% of their own denials (OIG, 2014–2016 data)
- Yet only 1% of denials were ever appealed — the system works and almost nobody uses it
- A later OIG review found 13% of denied prior-auth requests and 18% of denied payment requests met Medicare coverage rules — services that would have been paid under original Medicare
Under-appealing is a silent revenue leak. If your current setup writes denials off because “appeals aren’t worth the effort,” the data says the opposite: appeals are the highest-yield work in the revenue cycle.
Two Different Clocks — Conflating Them Writes Off Recoverable Money
Timely filing is the window to submit a claim; appeal deadlines are the windows to contest a denial. They are separate clocks per payer, and mixing them up is a classic write-off cause.
| Payer | Typical timely filing (from date of service) | The rule of thumb |
|---|---|---|
| Original Medicare (FFS) | 12 months | The most generous clock in the industry — 12 months, hard stop |
| Medicare Advantage plans | Per plan contract — commonly 90–180 days | Read the plan’s provider manual; MA clocks are routinely a fraction of FFS |
| Commercial payers | Per contract — commonly 90–180 days | Contract language controls; some plans 365, some as short as 90 |
| Medicaid | State-specific | Every state sets its own — verify per state, per program |
The write-off that wasn’t
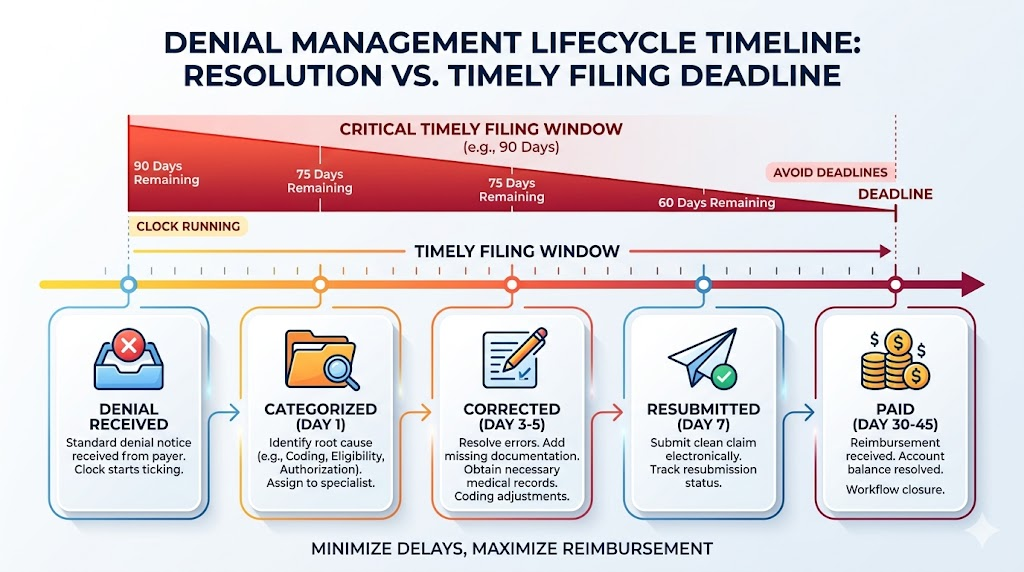
The classic loss: a denial arrives 60 days after submission under a commercial payer with a 180-day filing limit — still appealable, still fixable — but someone assumes “the deadline passed” and writes it off. Every open denial should carry two dates: its timely-filing expiry (relevant if a corrected claim is needed) and its appeal deadline (relevant if it’s contested). RevGen tracks both, per payer, per claim — automatically.
How the RevGen Denial Workflow Runs
Denial capture. Every denial flagged and categorized automatically by CARC code family — no denials discovered by accident months later.
Root-cause analysis. Coding issue, eligibility problem, auth gap, credentialing lapse, or documentation deficiency — named, not guessed.
Corrective action. Claim edit and resubmission, formal appeal with supporting documentation, peer-to-peer coordination for medical necessity, or credentialing follow-up — matched to the cause.
Deadline tracking. Both clocks — timely filing and appeal windows — tracked per payer, per claim. Nothing ages past a deadline silently.
Trend reporting. Monthly: which denial categories are falling, which are growing, by payer and code — with the dollar value of each.
Prevention loop. Denial data feeds back into pre-submission checks — the upstream edit that stops the recurring CO-4 or CO-197 pattern for good.
How Fast Does Recovered Revenue Arrive?
Simple denials — wrong modifier, retroactively obtainable auth — typically correct, resubmit, and pay within 30–45 days. Complex medical-necessity denials requiring peer-to-peer or full appeal run 60–120 days, depending on the payer.
The variable that actually matters
It’s not the payer’s speed — it’s how quickly the denial gets worked. A denial that sits 45 days before anyone looks at it has 45 fewer days in its appeal window. Our workflow assigns and works every denial within its first week.
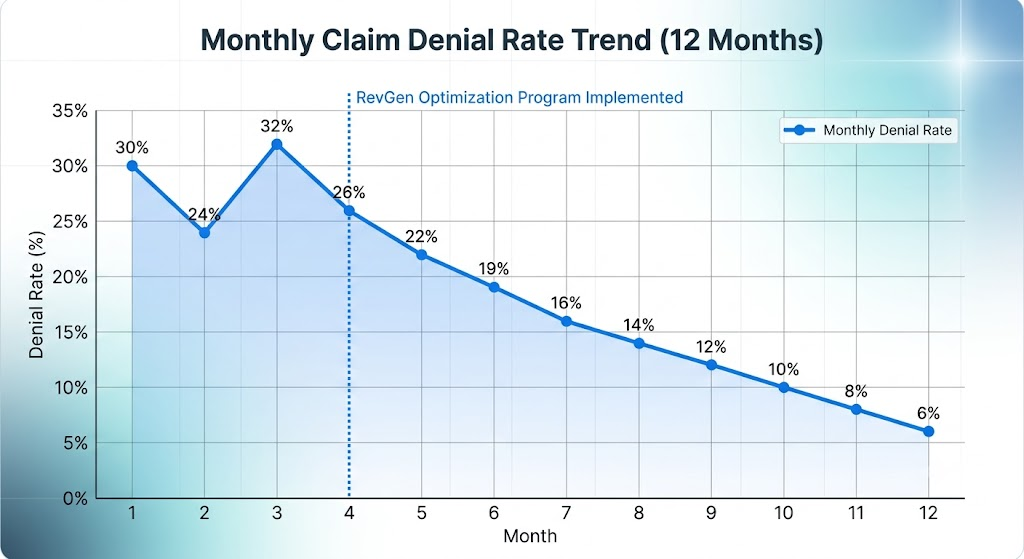
The Denial KPIs — With Formulas
| Metric | Formula | Target |
|---|---|---|
| Denial rate | Claims denied ÷ claims submitted, measured first-pass | < 5% |
| Overturn rate | Denials overturned ÷ denials appealed | Tracked vs. OIG benchmarks |
| Denial aging | % of open denials older than 90 days | → 0 |
| Category mix | Denial share by CARC family and payer | Downward, month over month |
Industry context, honestly framed
Across healthcare, denial rates run 5–10% of submitted claims; below 5% is strong. But the raw rate matters less than the mix — a 6% rate made of fixable front-end categories is a process problem you can eliminate; a 3% rate heavy in medical-necessity denials needs documentation work. Every number we report comes with its formula and is verifiable in your own system.
Where Denial Management Fits
Denials are the symptom layer of the revenue cycle — the pages below cover the rest of the system:
Frequently Asked Questions
What denial rate is considered good?
What changed for denials in 2026?
What happens if a denial goes past the timely filing limit?
Can previously written-off denials be recovered?
What is a CO-4 denial code and how is it fixed?
What are the Medicare appeal levels and deadlines?
Do denial appeals actually work?
What is the difference between a rejection and a denial?
Does RevGen handle appeals as well as resubmissions?
How does denial management differ by specialty?
What denial data should our reports show?
What’s the difference between timely filing and appeal deadlines?
Which Categories Are Your Denials Hiding In?
The free denial audit maps your denial pattern by CARC family, payer, and code; prices the recoverable dollars in aged A/R; and checks your appeal-position against the OIG benchmarks. In writing, yours to keep.
Request Your Free Denial Audit →✔ Every denial worked in its first week · ✔ Both deadlines tracked per payer · ✔ Appeals through all five levels