
Built for Practices Where the Physician Is Also the Billing Department
Small practices don’t lose revenue to bad coding — they lose it to the work that never gets scheduled: denials nobody circles back to, A/R aging past timely filing, Medicare advantages never claimed. RevGen runs that entire system inside your EHR, priced for your volume — per-claim or percentage, shown both ways.
- Every denial worked, every aging claim followed — the workflow your front desk never has time for, run as a dedicated system
- Small-practice Medicare advantages claimed — the +6 MIPS bonus, reduced reporting requirements, G2211 visit-continuity add-on — most small-practice billers miss all three
- Priced for your volume — per-claim often beats percentage at low volume; we show the math both ways, no minimum-fee traps
- Your EHR stays — 40+ platforms worked inside, from athenahealth and eCW to Tebra and SimplePractice, no migration ever
- 2026→2027 currency checks — charge-master checked against the CPT 2026 changes and the January 1, 2027 wave
- Free audit first — baseline numbers with formulas, gaps in writing, yours to keep
Why Small Practices Lose Revenue Before They Even Notice
Running a small practice means wearing too many hats at once. The physician is also the business owner. The front desk is also handling billing questions. And the person responsible for denied claims is already underwater with scheduling.

The most common revenue problem at small practices isn’t bad coding — it’s the total absence of a denial follow-up workflow. Claims go out, get denied, get marked “to follow up,” and quietly age past 90 days while everyone is too busy to circle back. By the time someone catches it, timely filing limits have expired. That’s real money written off — not from errors, but from no process. A dedicated billing operation closes that gap: every denial gets a response, every aging claim gets worked, and the write-offs that come from silence simply stop happening.
The three hats problem, in one sentence
When one person schedules, checks patients in, answers phones, posts payments, and works denials, the work that never gets done is always the work with no deadline attached — and that’s exactly what denial follow-up and A/R management are. Outsourcing doesn’t add staff; it adds a system that doesn’t depend on spare time existing.
What You Actually Get — The Full Revenue Cycle, Specifically
Generic service lists don’t help you decide. Here’s what changes hands, concretely — the same revenue cycle large groups buy, sized to your practice.
Eligibility before the visit
Real-time coverage, copay, and deductible checks run before appointments — because billing a lapsed plan is the fastest denial there is, and preventing it beats reworking it.
Specialty-accurate coding
Certified ICD-10/CPT/HCPCS coders who know your specialty’s nuances — the 99213-vs-99214 distance, when modifier -25 applies, when an E/M is separately billable alongside a procedure. Undercoding is more common than overcoding and costs the same.
Automated claim prep
Rule-based automation handles the repetitive pre-submission checks — missing fields, NPI formats, payer-specific requirements — so human effort goes to judgment calls, not keystrokes.
Root-cause denial management
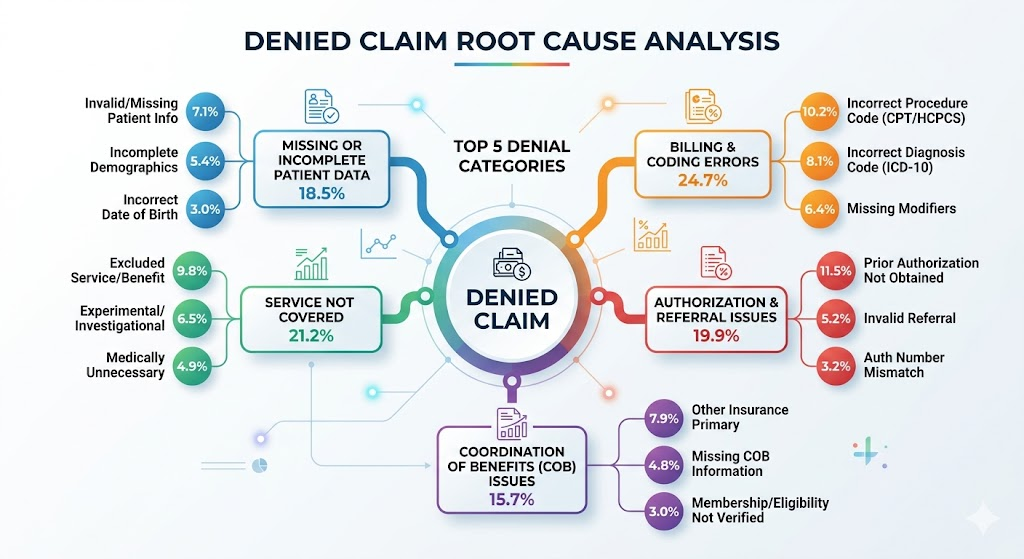
Denials tracked by payer, code, and provider — so the same denial doesn’t repeat month after month. Reactive re-submission is what most companies sell; pattern elimination is the job. (Details: denial management.)
Daily posting & ERA reconciliation
Payments posted daily and reconciled line-by-line — because one mis-posted ERA makes your A/R report fiction: you can’t tell what’s genuinely outstanding from what’s already paid. Underpayments flagged for appeal.
Credentialing kept current
Enrollments verified, renewals flagged 90 days ahead — one lapsed enrollment means a wave of denials from one payer, and small practices feel that wave at full force.
In-House vs. Outsourced — The 2026 Numbers, Not the Marketing Version
The honest comparison for a small practice isn’t “cost vs. cost” — it’s what each model actually delivers at your volume, and what breaks first.

| Factor | In-house billing (2026 reality) | Outsourced to RevGen |
|---|---|---|
| Monthly cost | A billing-capable staffer runs $45K–$60K+ salary (2026 market) plus a 25–30% benefits/overhead load — before software, clearinghouse fees, and training. At small volumes that’s often the most expensive biller-per-claim arrangement in medicine. | Per-claim, percentage of collections (typically 4–9%), or hybrid — sized to your volume, quoted after the audit, no setup fees |
| Denial follow-up | Depends entirely on spare time — which is why denials age past timely filing | Dedicated workflow; every denial worked, root-caused by payer and code |
| Clean claim rate | Unmeasured at most small practices — no baseline, no formula | Target ≥95% first-pass, defined as accepted-on-first-submission ÷ submitted, measured before rework, reported weekly |
| The single point of failure | One biller’s vacation, illness, or resignation stops your cash flow — and their knowledge leaves with them | A team with documented workflows; nothing pauses |
| Coding depth | Generalist staff; ongoing training is your problem and expense | Certified coders with your specialty’s rules — including the 2026→2027 code changes |
| Visibility | Whatever reports someone has time to build | Live dashboards: A/R aging, denials by payer, collections by provider |
| HIPAA posture | Entire compliance burden internal | BAA-defined obligations, named-user access, least-privilege roles — with the honest caveat that a BAA defines duties, it doesn’t transfer your legal risk |
| Scalability | Growing means hiring — the whole cost structure repeats | Volume scales without a hiring event |
Most-missed by small-practice billers
The Medicare Advantages Small Practices Fail to Claim
Medicare’s rules are written with structural breaks for small practices — and most small-practice billing setups never claim them. This is the section your current biller hopes you skip.
MIPS: the +6 you’re owed
Practices with 15 or fewer clinicians get a +6 point bonus on the final MIPS score, only one Improvement Activity instead of two, and more favorable reweighting when a category can’t be scored. Add the opt-in election and virtual groups (solo practices and groups of ≤10 banding together — elected before the performance year starts), and small practices regularly move from penalty range to safe.
G2211: the visit-continuity add-on
An additional Medicare payment for office visits with patients in an ongoing longitudinal relationship — the exact product a solo or small practice sells. Refined for 2026, routinely missed by billers who don’t work small-practice Medicare day in and day out. For primary-care-shaped practices it’s one of the biggest underbilling gaps the audit finds.
The Jan 1, 2027 code wave
CPT 2027 lands — and maternity global-period codes are deleted effective January 1, 2027, restructure and all. Stale charge masters turn into automatic denials overnight. A charge-master currency check in December is the difference between a quiet January and a denial storm.
Where these get claimed
All three are built into how we run the MIPS performance year and the free audit — MIPS position, G2211 usage, and charge-master currency are standing audit checks, not upsells.
Pricing for Small Practices — Including the Trap Nobody Mentions
Per-claim often best at low volume
A flat fee per claim. Costs scale linearly with billing, so a slow month costs less — and the number is easy to verify against your claim counts. For low-volume practices this is frequently the honest answer.
Percentage of collections
Typically 4–9% of what’s actually collected — aligned incentives, no charge for denials we rework. Best when volume is meaningful and service lines are mixed.
Hybrid
Base + reduced percentage — useful when you keep some front-end work in-house but want the back office fully covered.
⚠️ The minimum-fee trap, explained
Many percentage agreements carry monthly minimums. At low collections volume, the minimum — not the percentage — becomes the real price, and the effective rate you pay can run far above the headline number. A “4.5% of collections” agreement with a minimum fee can quietly cost a solo practice double-digit percentages in slow months. Ask any billing company to show the effective rate at your actual volume, in writing. We show that math in the audit quote, both models, before you commit to either.
Choosing a Billing Company — The Five Mistakes We See Repeatedly
After working alongside many practice managers evaluating vendors, these are the mistakes that cost the most:
1. Choosing on price alone
A low percentage with a weak first-pass rate and no denial follow-up costs more than a higher rate with a system. Run the math on your volume — and ask for the effective rate including any minimums.
2. Not asking for denial rates in your specialty
A company excellent in primary care may be weak in surgical or behavioral billing. Ask for denial-rate data specific to your specialty — and how they root-cause it.
3. Skipping the audit step
Any reputable partner offers a real audit before the pitch. If they won’t show you where your revenue gaps are before you sign, that tells you everything.
4. Ignoring reporting transparency
If you can’t see A/R aging, denial rate by payer, and collections by provider in real time, you’re flying blind — and “trust us” is not a dashboard.
5. Not verifying EHR integration — and data custody
Switching billers shouldn’t mean manual re-entry; confirm they work inside your actual system. And ask the question most practices never do: “when we part ways, where does our data live?” The right answer is “in your system, always.” If their answer involves exporting from their platform, your billing history is a future hostage.
What practice managers say matters most
A recurring theme in physician finance communities: the practices most satisfied with outsourced billing aren’t the ones that got the lowest rate — they’re the ones with the clearest onboarding process and the most responsive denial management. Transparency and communication outrank the percentage once you’re live.
Onboarding — Five Steps, Two to Three Weeks, No Migration
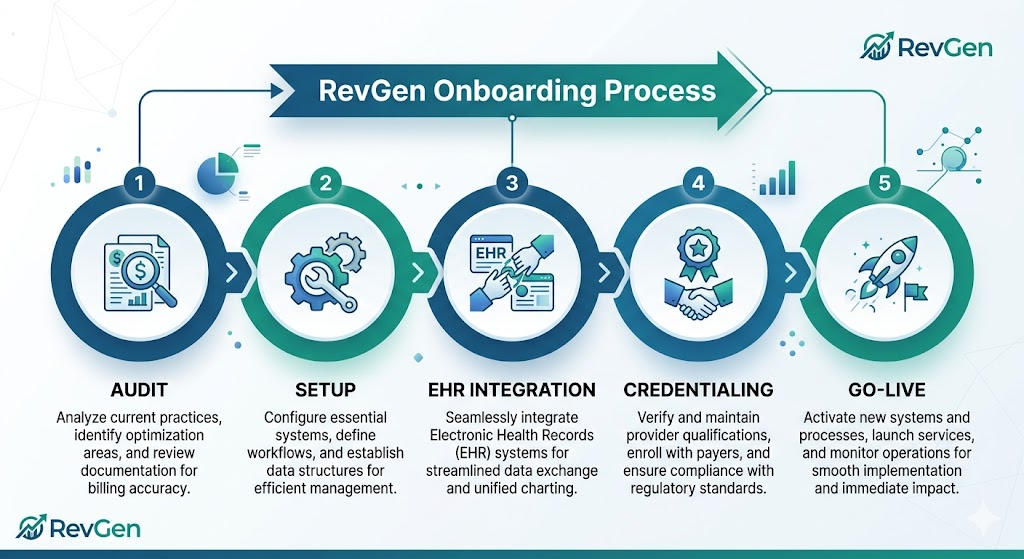
Free billing audit. Current setup, denial patterns, A/R aging, revenue gaps — baseline numbers with formulas, in writing, yours to keep.
Practice profile setup. Account configured around your specialty, payer mix, EHR, and provider roster.
Working in your EHR. No migration, no manual transfer — access is named-user, BAA-signed, least-privilege. You keep the audit trail.
Credentialing review. Gaps closed and renewals flagged before they become denials.
Go-live. Claims processing begins with dual QA on the first batches; dashboard access from day one. You get a real calendar date after the audit, sized to your payer count and legacy A/R.
Specialty Depth, Small-Practice Scale
Small doesn’t mean generic — each specialty carries its own code sets, payer rules, and 2026–2027 exposures. The audit checks against your specialty’s specifics:
Frequently Asked Questions
What clean claim rate should a small practice expect?
How is RevGen different from a typical billing company?
Does outsourcing billing work for a solo practice?
Can I keep my existing EHR?
How much do billing services cost for a small practice?
What are the small-practice MIPS advantages?
What is G2211 and why does it matter for small practices?
How long does it take to switch billing companies?
What improves first after switching?
Is RevGen HIPAA compliant?
What happens to our data if we leave RevGen?
What 2027 changes should small practices prepare for?
Twenty Minutes, Zero Cost, Your Numbers in Writing
The free audit baselines your clean claim rate, denial pattern, A/R aging, MIPS position, and G2211 usage — and checks your charge master against the January 2027 changes. You keep the report whatever you decide.
Request Your Free Billing Audit →✔ No obligation · ✔ Your current biller is never contacted · ✔ Findings in 24–48 hours